What Are these unmeasured cations
These unmeasured cations are positive components in the blood that are present but not typically included on a standard serum chemistry panel. They are important because the body maintains electrical neutrality: the total positive charge from cations must offset the total negative charge from anions. When clinicians review serum electrolytes, they usually see the major measured ions, but some ions are left out of the usual calculation.
The most familiar measured ions include sodium, chloride, and bicarbonate. These are the key values used to estimate the anion gap. The gap is a useful derived number in acid-base assessment because it provides a fast assessment at ion balance and can suggest whether hidden acids or other factors are at play.
In everyday practice, measured ions do most of the work in lab interpretation. Still, the smaller set of unmeasured cations can influence the result, especially when there is a major shift in serum concentration or when a patient has an unusual exposure or illness. That is why understanding these ions is useful for both laboratory interpretation and broader acid-base balance review.
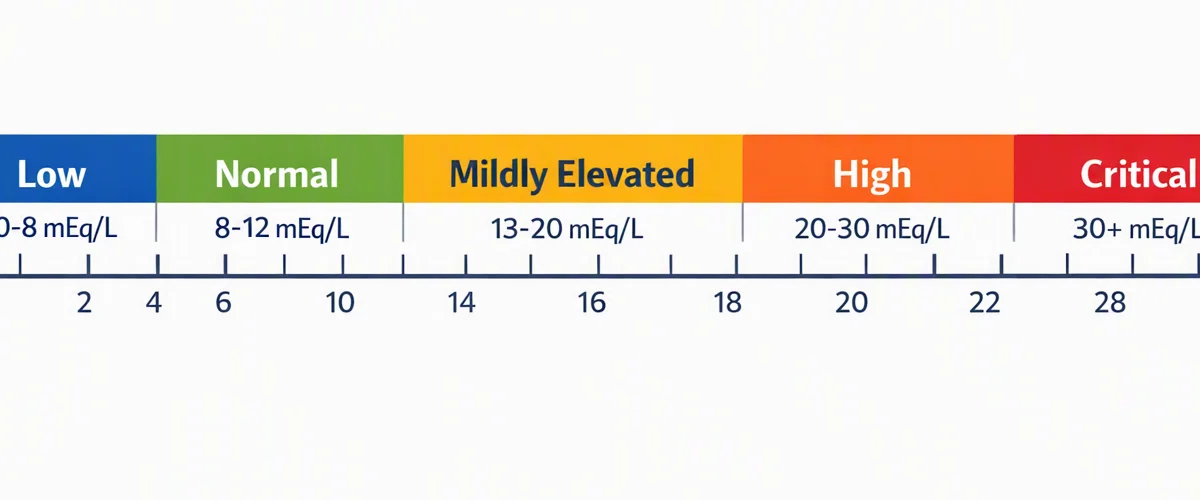
A basic metabolic panel gives the main electrolyte values, but it does not fully represent all charged species in plasma. The gap reflects what is not directly measured, including some anions and cations. Most of the time, the body’s buffer systems and ion distribution keep the effect small. However, in the right clinical setting, these missing cations become an important diagnostic clue.
What Frequent Cations Are Not Routinely Measured?
The most discussed usual cations that are not measured routinely are magnesium, calcium, potassium, and lithium. Each has a distinct function in bodily function, and every one affects the composition of blood in another way.
Potassium is often measured in routine laboratory assessment, but it is not part of the standard anion gap formula. Since its serum level is usually much lower than sodium, its omission rarely changes the calculation greatly. Still, extremely high or extremely low potassium can play a role in broader electrolyte disturbances and may alter the overall clinical picture.
Calcium is a further cation that is generally evaluated independently rather than added in the anion gap equation. Shifts in calcium can influence neuromuscular function and reflect systemic illness, but its direct effect on the gap is typically limited unless the abnormality is pronounced.
Magnesium levels often represents a issue in admitted patients, especially those with low intake, digestive losses, or kidney problems. High magnesium can act as an added positive charge load, but important changes in the anion gap are rare unless the elevation is severe.
Lithium serves as the key unmeasured positive ion from a laboratory interpretation standpoint because it may significantly alter the anion gap when presented in toxic amounts. In contrast to the others, lithium is a prescription medicine and possible poison rather than a standard electrolyte. Its positive charge can immediately shift ion balance and cause a reduced or even negative anion gap.
These positively charged ions are generally minor contributors under normal conditions, but they grow relevant when the reference range is surpassed or when there is an unusual acid base pattern. For that reason the question is not only which cations are lacking, but which ones are clinically significant.
How Hidden Cations Alter the Anion Gap
The anion gap is a derived estimate of the difference between routinely measured positive and negatively charged ions. As unmeasured cations rise, the balance can shift in a way that makes the gap appear lower. This is because extra positive charge lessens the space left for unmeasured anions in the equation.
This link becomes especially important in acid-base balance. For instance, in metabolic acidosis, a high anion gap often suggests the accumulation of acids. Yet if the patient also has a significant cation load or low albumin, the result can be misleading unless the full picture is reviewed.
Albumin deserves special attention because it is a major negatively charged plasma protein. Low albumin reduces the expected anion gap, which can mask an underlying acid-base problem. In other words, a normal gap is not always reassuring if albumin is low. At this point a corrected anion gap becomes useful in laboratory interpretation.
Unmeasured cations matter because they can obscure what is happening with hidden acids, buffer systems, and plasma proteins. They do not usually create major issues in healthy individuals, but they can alter the numerical result enough to change clinical thinking. For that reason the gap should be interpreted as part of a full acid-base assessment, not as a standalone answer.
In practical use, if the gap is unexpectedly low, clinicians may think about extra cation load, low albumin, or both. If the gap is high, the focus shifts toward acid accumulation, though unusual cation shifts can still complicate interpretation. The core idea is simple: ion balance is dynamic, and the anion gap is only one window into that balance.
When to Suspect an Elevated Unmeasured Cation Load
An elevated unmeasured cation load is most important to consider when the test pattern does not fit the patient’s condition. The concern rises if there is toxicity, kidney disease, or a clear electrolyte imbalance that is not fully explained by the usual measured ions.
Impaired kidney function is a common setting because impaired renal function can disrupt excretion of multiple electrolytes and cause renal failure-related shifts in serum concentration. In this situation, both cation and anion handling may shift. The result can be a puzzling pattern that requires careful review rather than a quick conclusion.
Toxicity is another important clue. Lithium exposure exposure can produce a low anion gap and should be considered when there is a compatible medication history or altered mental status. This is an example of how a specific cation can serve as a strong diagnostic clue, especially if the lab pattern appears discordant with the clinical picture.
A significant acid-base disturbance can also point to a hidden ion problem. If a patient has symptoms of systemic illness, unexpected lab changes, or worsening acid-base disturbance, the possibility of unmeasured cation contribution should be kept in mind. These situations often need careful review of the full metabolic panel and repeat testing if needed.
Other signs that deserve attention include https://anion-gap-lookup194.theburnward.com/anion-gap-calculator-for-differential-diagnosis-of-acidosis new confusion, weakness, arrhythmia concerns, or a sudden change in a previously stable electrolyte profile. In those cases, the issue is not just the number on the page. It is the possibility that the reported result reflects a broader disturbance in ion balance or a developing toxic or renal process.
Common Causes of Low-Range or Normal Anion Gap
A low or normal anion gap does not always mean the patient is well. Among the most frequent causes is hypoalbuminemia. Since albumin is a primary negatively charged protein, low levels decrease the calculated gap and can conceal another process. This is why albumin should always be checked when evaluating the result.
Lab error is also a frequent cause. A specimen problem, analytic issue, or data entry problem can alter the measured ions and create an apparently abnormal gap. If the number does not fit the patient’s condition, repeating the test is often the first step in responsible laboratory interpretation.
Paraproteinemia is an important but less common cause. Abnormal plasma proteins, especially in monoclonal gammopathies, can change charge distribution and affect the apparent balance between measured ions. Because these proteins are part of the broader pool of plasma proteins, they can influence the gap in a way that points to an underlying blood-related disorder.
A unchanged anion gap can also be seen when there is no major acid-base problem, when the cation and anion shifts cancel each other out, or when the abnormality is mild enough to fall within the reference range. That is why the result must be interpreted with symptoms, medication history, kidney function, and albumin level in mind.

In short, a reduced or normal gap is often explained by one of three broad ideas: low albumin, lab error, or abnormal proteins. A clinically guided interpretation helps separate benign variation from important disease.
How to Read Results with an Anion Gap Calculator
An anion gap calculator is a practical tool for quick assessment of electrolyte data. It usually uses sodium, chloride, and bicarbonate to calculate the gap. Because these values come from the standard chemistry panel, the calculator provides a quick snapshot of the current ion balance.
To use it well, initially confirm that the input values are right and belong to the same sample. Small transcription errors can make the result misleading. Next, compare the output to the expected reference range used by the laboratory or institution. Different methods and analyzers may produce slightly different results, so the exact cutoff matters.
If the result is low, think through common explanations: hypoalbuminemia, lab error, excess cation load, or paraproteinemia. If the result is high, consider whether the patient has metabolic acidosis or another process that increases unmeasured anions. The number alone is not the diagnosis; it is a starting point for acid-base assessment.
It also helps to review the trend of chloride and bicarbonate. A low bicarbonate often points toward metabolic acidosis, while chloride changes may indicate compensation or a non-gap pattern. Pairing the result with albumin allows a more accurate corrected anion gap, especially in patients with systemic illness.
Use the calculator as part of a broader clinical reasoning process. Ask whether the result fits the symptoms, medication list, kidney function, and other measured ions. That approach makes the calculator more than a number generator; it becomes a tool for more accurate laboratory interpretation.
A useful anion gap result is not just about calculation. It is about matching the number with the patient’s condition, the serum electrolytes, and the likely acid-base disorder.
In practical terms, if the gap is unexpected, review the underlying values first, then assess whether albumin correction is needed, then consider uncommon cations or toxic exposures. This sequence helps avoid missing a hidden diagnosis.
Common Questions
What are the main unmeasured cations?
The most commonly discussed unmeasured cations are magnesium, calcium, potassium, and lithium. Potassium and calcium are frequently measured separately, but they are not part of the classic anion gap formula. Lithium is the most relevant unusual cation because it can significantly affect the anion gap when present in toxic amounts.
Why do unmeasured cations matter during an anion gap calculation?
They matter because the anion gap is based on measured ions only, mainly sodium, chloride, and bicarbonate. Extra positive charge from unmeasured cations can lower the apparent gap and change laboratory interpretation. This can influence acid-base assessment, especially when there is hypoalbuminemia, kidney disease, or a possible toxic exposure.
Can lithium cause a low or negative anion gap?
Yes. Lithium is a classic cause of a low or even negative anion gap when serum levels are high enough. Because it is a positively charged ion that is not routinely included in the calculation, it can significantly shift ion balance. If the result is unexpected and lithium exposure is possible, toxicity should be considered promptly.
Does calcium or magnesium significantly change the anion gap?
Usually not by much. Calcium and magnesium can act as unmeasured cations, but they typically do not alter the anion gap dramatically unless the abnormality is severe. Their clinical importance is greater for electrolyte disturbances and overall acid-base balance than for routine gap calculation.
What should you do if the anion gap result seems unexpected?
First, confirm the electrolyte values and consider repeating the test if lab error is possible. Then check albumin, review chloride and bicarbonate, and think about kidney disease, paraproteinemia, or toxicity. If the clinical picture suggests an acid-base disorder or a major electrolyte imbalance, further evaluation is warranted rather than relying on the number alone.