What the Anion Gap Indicates
The anion-gap is a calculated value used to assist interpret blood electrolytes and understand how the body is maintaining acid and base balance. An Anion Gap Calculator determines the serum anion gap from routine blood chemistry values, usually sodium, chloride, and bicarbonate. This provides a practical tool for fast clinical interpretation of an electrolyte test.
The calculation helps identify whether there may be excess hidden anions in the blood. These are substances not directly shown on a standard chemistry report but that still influence the overall charge balance. When the gap is high anion gap, it can point toward conditions such as acidotic states. When it is decreased anion gap, it may suggest issues such as low albumin, laboratory problems, or other less common causes.
Because the anion gap is derived from everyday lab values, it is widely used as a checking and tracking measure rather than a standalone diagnosis. It gives context to other findings and can help narrow the differential in an acid-base imbalance. In short, it is a quick way to calculate anion gap https://anion-gap-help366.lucialpiazzale.com/can-diabetes-lead-to-a-elevated-anion-gap results and connect them to broader physiology.
Using the Anion Gap Calculator
Using an Anion Gap Calculator is straightforward. You input the relevant input values from the laboratory report: serum sodium, serum chloride, and plasma bicarbonate. The tool then uses the anion gap formula and displays the calculator result.
Many calculators are built for fast review of routine electrolytes. Some may also let you enter albumin for a corrected anion gap, which can be important when protein levels are abnormal. This is important because albumin is one of the major unmeasured negatively charged substances in blood chemistry.
To use the calculator well:
- Type in the exact numbers shown on the lab report. Verify the units match the calculator’s expected format. Determine whether the tool uses a standard or albumin-adjusted calculation. Look over the normal range shown by the calculator or your lab source.
The output should be interpreted in context. A single number may look normal, but if the patient has symptoms or other abnormal lab values, the overall picture may still point to a clinically important problem. Likewise, a mildly abnormal result may be less concerning if it fits the expected picture of the patient’s condition.
Anion Gap Formula and Interpretation
The standard anion gap formula is expressed as Na minus Cl minus HCO3. Simply stated, it means taking chloride and bicarbonate away from sodium. This simple formula estimates the difference between commonly measured positive and negative ions in the blood.
The usual logic is that sodium is the main measured cation, while chloride and bicarbonate are the main measured anions included in the calculation. This gap reflects the charge contributed by unmeasured ions. A within-range or normal anion gap suggests a fairly balanced pattern of measured and unmeasured ions, while a shift in either direction can reveal a hidden disturbance.
One important adjustment is albumin correction. Albumin plays a major role in the anion gap because it carries negative charge. When albumin is low, the measured gap may appear artificially reduced. A corrected anion gap can therefore better reflect true physiology in certain patients.
An elevated anion gap often suggests increased unmeasured acids in the blood, which is a major clue in metabolic acidosis. A low anion gap is uncommon, but it can be clinically meaningful when it reflects hypoalbuminemia, excess positively charged proteins, or technical error.
Consider the anion gap a clue, not a diagnosis. It can help show whether the blood chemistry pattern suggests hidden acids, protein shifts, or a measurement problem.
Common Causes of a raised anion gap
A elevated anion gap usually indicates there are extra acids or unmeasured anions in the bloodstream. This result is especially important in metabolic acidosis, where acid buildup lowers bicarbonate and changes the overall electrolyte picture.
Typical causes include:
- Lactic acidosis, where lactate rises because of poor oxygen delivery, shock, sepsis, or other stress states. Ketoacidosis, including diabetic ketoacidosis, alcoholic ketoacidosis, or starvation-related ketosis. Renal failure, where the kidneys cannot clear acids effectively. Toxic ingestion, such as exposure to substances that generate acid metabolites or interfere with normal metabolism.
These causes are important because they point to very different treatments. For example, lactic acidosis may require urgent stabilization and correction of the underlying cause, while ketoacidosis requires insulin, fluids, and careful electrolyte management. In renal failure, impaired acid elimination and electrolyte handling often drive the abnormal result. With toxic ingestion, the pattern may be a critical diagnostic clue.
The calculator result alone does not tell you which cause is present. It only highlights that there may be extra unmeasured anions, prompting further review of the patient’s symptoms, lab results, and acid-base status.
Typical Causes of a Decreased Anion Gap
A reduced anion gap is rarer than a high one, but it can still be significant. The leading explanation is hypoalbuminemia, since low albumin eliminates a major source of negative charge from the measured system. In many cases, this is why albumin correction is so important.
Other frequent causes include:
- Lab error, which is always worth keeping in mind if the result does not match the clinical picture. Paraproteinemia, where abnormal proteins create unusual positive charge patterns. Hyperchloremia, which can reduce the calculated gap by shifting the relationship between sodium, chloride, and bicarbonate.
A low gap may also be seen when the measurement technique or specimen handling influences the reported values. Because of that, a repeat panel is sometimes needed before concluding that the result reflects a true disorder. Reviewing the reference range and the patient’s overall status helps determine whether the low result is clinically relevant.
When hypoalbuminemia is present, the apparent low gap may not indicate a true acid-base problem. Instead, the value may simply indicate reduced albumin concentration. That is why the serum anion gap should always be interpreted with the protein level in mind.
Constraints of the Calculator
An Anion Gap Calculator is helpful, but it has important limitations. First, the result depends on the accuracy of the entered lab values. If the sodium, chloride, or bicarbonate measurement is incorrect, the calculated gap will also be off. Even slight shifts in the input values can change the result.
Second, calculators may use slightly different reference range cutoffs depending on the laboratory or method. That means a value considered normal in one setting may be on the edge in another. Some calculators also use different assumptions about whether potassium is included, which can affect the interpretation slightly.
Third, albumin can significantly affect the interpretation. A calculator that does not include albumin may miss a true abnormality or make a low value look more alarming than it is. A corrected anion gap can improve interpretation, but it still does not replace full clinical assessment.
Likewise, the anion gap is only one piece of the puzzle. It does not replace an arterial blood gas when a thorough evaluation of pH, carbon dioxide, and compensation is needed. It also does not identify the specific cause of an abnormality. It provides diagnostic support, not a final diagnosis.
In the end, the calculator must be interpreted in clinical context. Symptoms, medication history, kidney function, nutrition status, and other chemistry results all influence what the number means. A result can be normal and still miss a developing problem, or it can be abnormal without indicating an emergency.
When to Seek Medical Interpretation
If the calculator shows a significant shift, medical review is important. An abnormal Anion Gap Calculator can signal an acid base disorder, especially if it is combined with low bicarbonate, abnormal pH, or alarming symptoms. This is especially true when the pattern suggests metabolic acid buildup.
Expert interpretation is also valuable when there is a wider electrolyte imbalance. Because the result depends on the relationship among sodium, chloride, and bicarbonate, other disturbances in electrolyte levels can change the meaning of the number. A value that seems modestly abnormal may become more concerning if the person is dehydrated, critically ill, or has kidney dysfunction.
You should seek a clinician for interpretation when:
- The value is obviously above or below the expected range. There are symptoms such as disorientation, rapid breathing, vomiting, weakness, or severe fatigue. The patient has diabetes, kidney disease, suspected poisoning, or another major illness. The calculator suggests a high anion gap or low anion gap that does not match the clinical picture.
The anion gap in serum is most useful when viewed as part of a fuller assessment. In practice, it often directs the next step: repeat testing, albumin adjustment, blood gas analysis, or investigation for a specific cause of acidosis or protein abnormality.
Frequently Asked Questions
What counts as a normal anion gap?
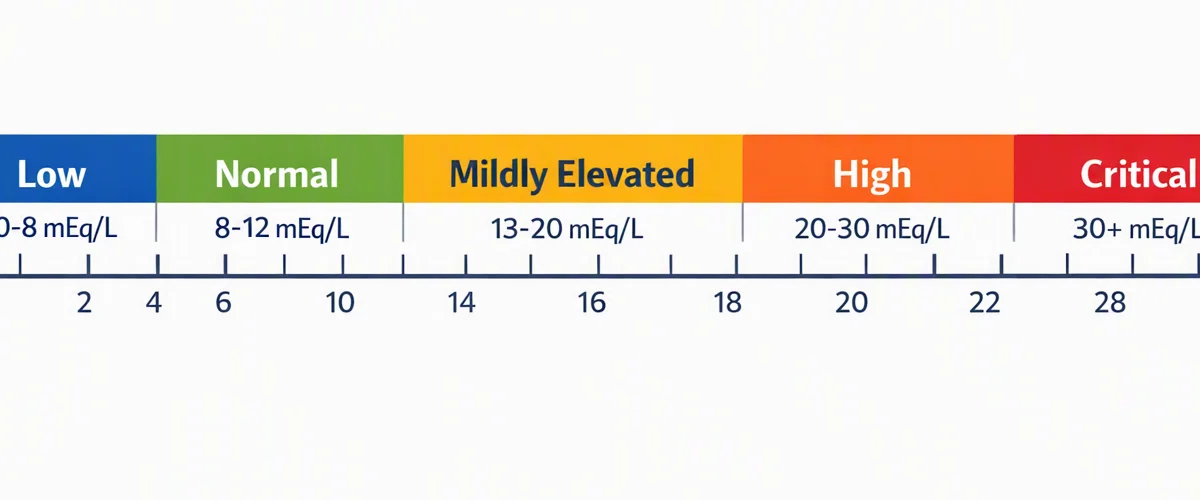
The anion gap normal range varies by laboratory method and the tool used. Most references consider a standard result to fall within a relatively narrow reference range, but the specific threshold should be taken from the laboratory report or the calculator itself. The key point is to review the result with the range attached to the specific reported values being interpreted.
How do you work out the serum anion gap?
You calculate the serum anion gap using the calculation formula: sodium minus chloride minus HCO3. In real use, you type in the measured serum sodium, chloride, and bicarbonate into an Anion Gap Calculator. The calculator then returns the gap as a brief overview of the balance between measured and unmeasured ions.
What does a high anion gap mean?
A high anion gap usually points to excess unmeasured anions from an acid load, which often points to acid-base acidosis. Frequent causes include lactic acidosis, ketone acidosis, kidney failure, and toxic ingestion. The result is a clue that should be interpreted alongside symptoms, kidney function, and other chemistry findings.
Is albumin correction needed for the anion gap?
Yes, correction for albumin can be very helpful when albumin is low. Since albumin is a major negatively charged protein, low levels can make the anion gap appear falsely low. A corrected anion gap may give a more reliable picture of acid-base status, especially when there is suspected metabolic acidosis or unexplained abnormalities in the electrolyte panel.
How reliable is an Anion Gap Calculator?
An Anion Gap Calculator is generally reliable for the arithmetic calculation, but its usefulness depends on the quality of the input and the broader overall interpretation. It can reliably compute the number from lab values, but it cannot determine the cause of an abnormal result on its own. Accuracy also depends on whether the calculator accounts for albumin, uses the correct expected range, and reflects the same method as the lab report. For that reason, it is best used for medical guidance, not as a substitute for medical evaluation.